


Retroverted (Tilted) Uterus: Symptoms, Myths, and When It Matters
Explore the link between a retroverted uterus and endometriosis/adenomyosis. Learn about symptoms, myths, and when it matters for your health.
10 minute read
Read moreDiscover how Lotus can guide you toward lasting relief.
Explore why patients choose Lotus
Search expert-written answers, browse by topic, or find information based on where you are in your journey.
Explore All KnowledgeReach out and start your healing journey.
Schedule an AppointmentEndometriosis truths and fact checking is difficult, if not seemingly impossible. Cut through confusion with evidence-based answers, correcting common myths about endometriosis and adenomyosis—from symptoms after menopause to HRT safety and surgical choices—to help you make informed decisions with your care team.
Endometriosis and adenomyosis live in a fog of gaslighting myths that delay diagnosis and push people toward unhelpful choices. This resource separates evidence from assumptions: what imaging can and can’t show, why pain that disrupts school or work isn’t “normal,” and how treatments—from hormonal therapy to excision—actually work best together. It also clarifies where the conditions differ: endometriosis grows outside the uterus, while adenomyosis occurs in the uterine muscle, so surgical decisions and fertility implications diverge.
Expect clear, practical explanations you can use in appointments: when a hysterectomy makes sense (often for adenomyosis, not endometriosis alone), why pregnancy or menopause rarely “cure” disease, and what realistic goals look like for pain, fertility, and long‑term health. Short guides point to deeper dives in Diagnostics & Imaging, Surgery, Medical Management, Fertility & Reproductive Health, and Menopause & Hormonal Transitions. Learn to spot red flags for look‑alike or coexisting issues in Related Conditions and when specialty teams improve outcomes, supporting confident, timely decisions without overtreatment or undertreatment.
It depends on what kind of treatment you mean, because treating endometriosis itself and managing endometriosis pain don’t always improve on the same timeline. Symptom-focused plans (like pain management strategies) can change how you feel relatively quickly, while disease-directed approaches may take longer to bring steady, day-to-day relief. Even after technically successful treatment, pain can persist if the nervous system has become sensitized, so we look at the full picture rather than using one symptom as the only measure.
In general, we recommend judging progress by patterns over time: your flare frequency, intensity, function (sleep, work, activity), and how predictable your cycles and triggers feel, rather than one good or bad week. Tracking symptoms helps us see whether you’re trending in the right direction or whether we’re simply masking pain while the underlying drivers remain. If you’ve been cycling through treatments without durable improvement, our team can review your records and symptoms, clarify what the treatment is truly targeting, and outline a reasonable trial period and next step for your specific situation.
Dr. Vasilev practices full-time helping patients with endometriosis. He is also a fellowship-trained gynecologic oncologist and an expert in MIGS surgery. That background doesn’t mean his current practice focuses on cancer care. It reflects very advanced surgical training in complex pelvic anatomy and challenging operative situations, including scar tissue and recurrent disease. Beyond the training that average gynecologic oncologists receive, he has additional training and experience gained from mentors in urologic oncology and general surgery, as well as extensive ten-year experience in collaborative multidisciplinary surgeries as Director at the City of Hope.
That expertise translates directly to endometriosis and adenomyosis surgery, where it’s often critical to operate safely around the ureters, bowel, bladder, nerves, and major blood vessels, and to make sound decisions in densely scarred tissue. Today, our team’s work is dedicated entirely to endometriosis and adenomyosis care, and we welcome you to reach out if you’d like to discuss your symptoms and surgical options.
No, out-of-network care doesn’t automatically mean you’ll pay 100% of the cost. Many plans still offer out-of-network benefits, and what you owe depends on the details of your specific coverage and the type of care you receive.
Our team can help you understand the financial side of moving forward, including what information to ask your insurer for and what documentation may be needed. If you’d like, contact us to schedule a consultation, and we’ll walk you through the process based on your situation.
Before we schedule your consultation, our team completes a brief preliminary review to understand what you’re experiencing and what information is already available. This typically includes reviewing your symptoms and any medical records you’ve shared, so we can guide you to the right next steps.
If your history and goals appear to be a good fit for the care we provide, we’ll schedule your consultation and outline what to expect from the process. If we need anything else to make that decision, such as additional records or clarification, our team will let you know so we can keep things moving efficiently.
Endometriosis isn’t one uniform condition, so study results can vary depending on which lesion types and locations are included, how advanced the disease is, and whether participants have had prior hormonal treatment or surgery. Many studies also rely on small or highly selected groups, which can make findings look stronger or weaker than they are in real-world patients.
Research teams may also use different diagnostic standards, define outcomes differently (pain scores, quality of life, or fertility), and follow patients for different lengths of time, so they’re not always measuring the same thing. When we interpret research with patients, we look for results that hold up across larger, more diverse groups and, when possible, well-designed randomized trials, because those results are more likely to reflect what you can expect in care.
Some people with pelvic pain, bloating, or bowel symptoms notice improvement when they reduce gluten and/or dairy, especially if those foods consistently trigger discomfort for them. Others don’t see a meaningful change, so there’s no universal endometriosis diet that fits everyone.
We typically encourage an individualized approach: paying attention to symptom patterns, making one change at a time, and choosing changes you can maintain without feeling restricted or under-fueled. If your symptoms are significant or you’re unsure whether they stem from a food trigger or an underlying endometriosis or adenomyosis issue, our team can help you sort that out and discuss next steps.
Patient stories can be incredibly helpful for naming symptoms, spotting patterns, and feeling less alone, but they’re not a forecast of what will happen in your body. The most reliable way to use them is to focus on the reasons behind someone’s experience (what symptoms led them to seek care, what was found, what choices they made), rather than assuming the same diagnosis or outcome applies to you.
Expert opinions are useful, but they’re still interpretations based on the information available and the clinician’s experience. We encourage you to use expert commentary to form precise questions about your own situation: what diagnoses are being considered, what evaluations actually clarify them, what risks and tradeoffs matter for you, and what a reasonable plan looks like if symptoms persist. If you’re sorting through conflicting stories or advice, our team can help you turn what you’re reading into an individualized next-step plan and decide what’s most relevant for your case.
It’s common to hear different treatment recommendations for the same symptoms because pelvic pain conditions like endometriosis and adenomyosis can look similar on the surface but have very different underlying drivers. The location and depth of disease, the presence of adhesions or ovarian cysts, and whether symptoms are more cyclic, constant, or related to specific organs can all change which approach makes the most sense. Research also doesn’t always compare options directly in a way that clearly fits an individual patient’s situation.
Recommendations also vary because clinicians are trained in different frameworks: some focus primarily on medical suppression of symptoms, while others emphasize identifying and removing disease. The tools available to them, including the quality of imaging and their comfort interpreting it, and your goals (pain relief, fertility planning, medication tolerance, or wanting a definitive diagnosis) can reasonably lead to different best next steps. If you’re getting mixed messages, our team can help you make sense of the possibilities and build a plan that matches your symptoms, priorities, and long-term goals.
Explore the link between a retroverted uterus and endometriosis/adenomyosis. Learn about symptoms, myths, and when it matters for your health.

Feeling dismissed with your endometriosis concerns? Discover expert insights on navigating healthcare while seeking validation and appropriate care.

Discover the truth about endometriosis and adenomyosis symptoms. Understand how common they really are, and gain insights for effective advocacy.

Explore the latest research on MCAS and its connection to endometriosis pain. Understand the implications for symptoms and treatment options.

Explore how to navigate Instagram for endometriosis and adenomyosis support while ensuring you receive accurate and trustworthy health information.

Understand how endometriosis affects ovarian, breast, thyroid, and cervical cancer risk, plus symptoms to watch, screening guidance, and ways to lower risk.
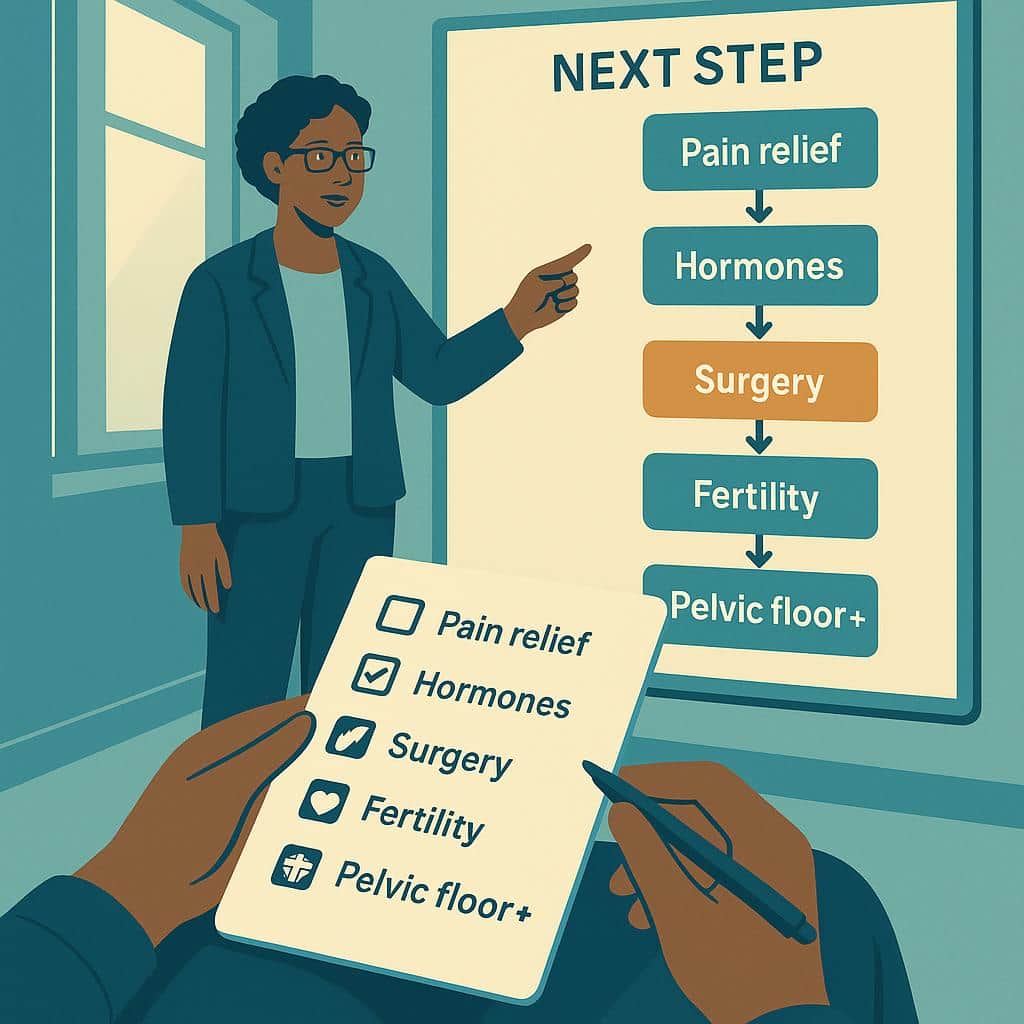
Part 2 demystifies endometriosis treatment confusion, reviews major guidelines, and distills evidence-based recommendations you can use.
Part 1 clarifies myths in endometriosis care: where surgery helps, what medical management can and can’t do, and how complementary therapies fit into a plan.

Learn about postmenopausal endometriosis: who is at risk, diagnosis and treatment basics, and why malignant transformation is rare but worth knowing.

Understand postmenopausal endometriosis: why it can persist, symptom management, HRT and phytoestrogen safety, and when surgery is appropriate.
Lotus Endometriosis Institute provides California-based surgical evaluation and advanced excision care for patients with suspected endometriosis, adenomyosis, complex pelvic pain, and related conditions.
Many patients contact us from outside California to learn whether traveling for in-person evaluation and possible surgery may be appropriate.
2121 Santa Monica Blvd, Santa Monica, CA 90404
8am - 5pm
Monday - Friday
154 Traffic Way, Arroyo Grande, CA 93420