


Deep & Complex Endometriosis Surgery
When endometriosis grows deep, reaches the bowel, bladder, ureters or diaphragm, or comes back after surgery, it needs one surgeon who can treat every organ involved, in one planned operation.
- Who operates
- Gynecologic oncologist, endometriosis expert
- Organs treated
- Bowel, bladder, ureters, diaphragm
- How
- Robotic, in one operation
Medically reviewed by Dr. Steven Vasilev, MD
Quadruple board-certified in surgical and integrative therapies, Minimally-Invasive Robotic Endometriosis-Excision Surgeon, Director of Lotus Endometriosis Institute · Updated Oct 2026
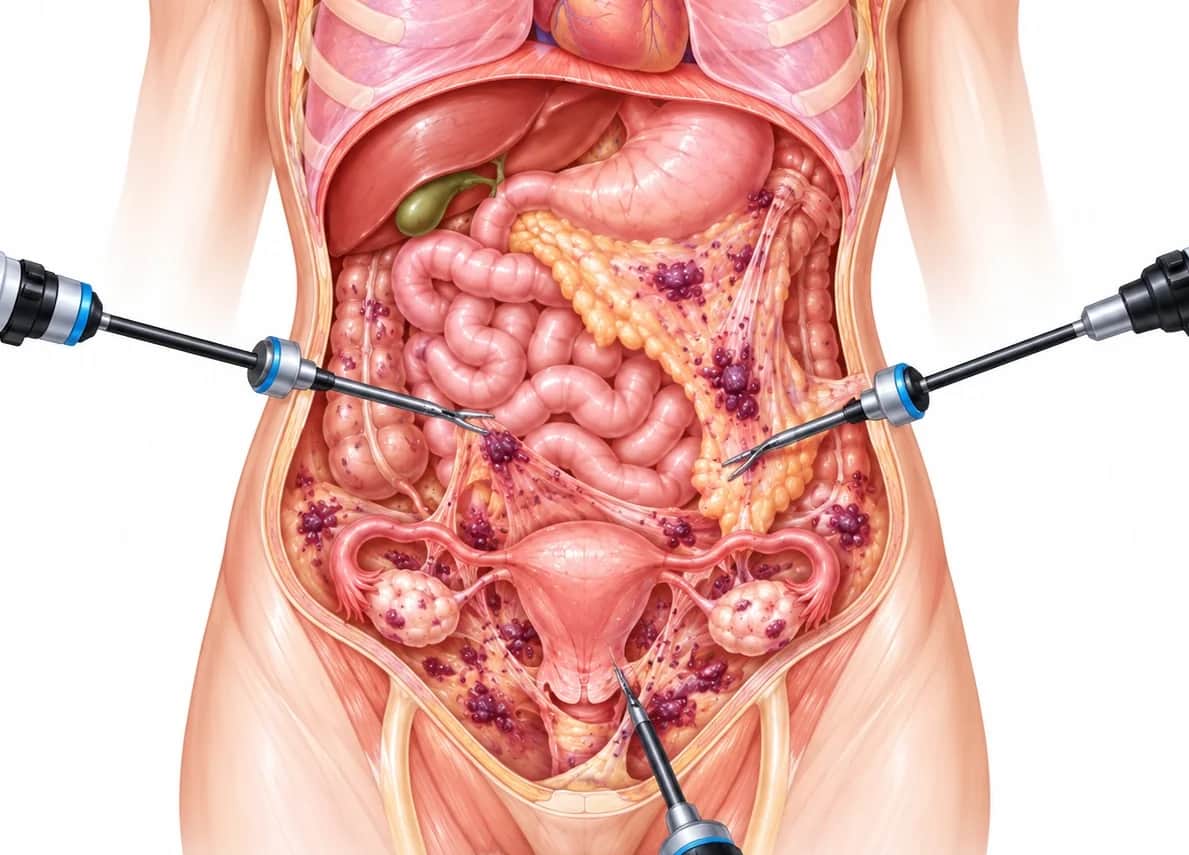
Tap a spot to see its surgery.
Is my case deep or complex?
When it grows below the surface, reaches the bowel, bladder, ureters or diaphragm, has spread widely, or came back after surgery.
Usually worth considering if
- Bowel or bladder pain that follows your cyclePain with bowel movements or urination, or urgency, that flares around your period.
- Imaging shows deep nodulesOn MRI, or an ultrasound done by an endometriosis expert.
- Shoulder or chest pain with your periodIt can point to disease on the diaphragm.
- Stage 4, or a "frozen pelvis"Organs stuck together by scar tissue.
- It came back after surgeryPain returned, or disease was left behind.
- Large or returning cystsEndometriomas that keep coming back, or look unusual.
Where is it, and which surgery?
Each organ has its own surgery and its own page. Many complex cases involve more than one, treated in the same operation.
- 1Bowel endometriosis surgeryShaving, disc excision or removing a short segment, sparing the bowel whenever possible.
- 2Bladder & ureter endometriosis surgeryRemoving disease from the bladder wall and freeing the ureters, protecting kidney and bladder function.
- 3Diaphragm endometriosis surgeryDisease above the liver, often found only during surgery. Few gynecologic surgeons operate here.
- 4CytoreductionFor the most advanced disease across many organs, or when cancer is a concern.
- 5Repeat surgery & second opinionsStill in pain after surgery? Why it happens, and what a second look can find.
How is complex surgery planned?
Everything is mapped and agreed before the day, so it's one operation, not two.
Before surgery
Planning consultation
By video, with every imaging, operative and pathology report you have, and your goals.
Mapping the disease
Specialized imaging, such as MRI or an ultrasound done by an endometriosis expert, often shows how deep the disease goes and which organs it touches. Other tests as needed.
More about Mapping the disease
Imaging helps plan the safest approach; the exact plan is confirmed during surgery. Disease on the diaphragm is often seen only then.
Your plan
What the operation may include, organ by organ, and your consent in advance to everything that might be needed, so it doesn't stop halfway. Insurance and a fixed price are settled before anything is booked.
Surgery day
One operation
Robotic, through small incisions. All the disease is removed, sparing organs whenever possible, with other specialists joining when needed.
In the hospital
Most often it is still a same-day outpatient procedure. When it isn't, how long you stay depends on which organs were treated, and how.
Recovery
Recovery
Usually several weeks, and longer after bowel or bladder surgery. Each organ's page has the details.
Follow-up
- 3 months
Follow-up
Your pathology results and a video check-in, with pelvic floor or pain care if you still need them.
Who should do it?
A surgeon who can operate on every organ involved, in one operation, and handle anything unexpected.
Many surgeons stop when endometriosis reaches the bowel, bladder or diaphragm, or bring in another surgeon who may remove more than needed. Dr. Vasilev is a gynecologic oncologist, trained for the most extensive pelvic and abdominal surgery, who focuses on endometriosis.
“Most of the work in a complex case happens before the operation: assessing where the disease is, and agreeing on what to do about it.”
Patients often ask
What surgery treats deep infiltrating endometriosis (DIE)?
The primary surgery for deep infiltrating endometriosis (DIE) is laparoscopic excision, sometimes with robotic assistance, to remove deep nodules. The goal is thorough removal while protecting nearby organs and pelvic nerves whenever possible.
Can imaging predict if I’ll need bowel, bladder, or ureter surgery?
Yes, high-quality pelvic ultrasound and MRI can often help anticipate whether bowel, bladder, or ureter surgery may be needed. Imaging helps plan the safest approach, but the definitive assessment and exact surgical plan are confirmed during surgery.
How is multi-organ endometriosis treated without organ removal?
In many multi-organ cases, conservative surgery removes endometriosis and frees organs from scar tissue while preserving the organs themselves. Robotic excision can improve precision, and treatment planning may include other surgical specialists.
Why is diaphragmatic endometriosis often found only during surgery?
Diaphragmatic endometriosis is frequently missed before surgery because standard exams and imaging focus on the pelvis, and some lesions are hard to see. Surgery allows direct inspection of the diaphragm, which can reveal implants that scans miss.
You’re on step 1 of 3
Next: Who should operate?What to look for in any surgeon, and Dr. Vasilev’s results.